Leaderboard
728x15
Showing posts with label CMS. Show all posts

Dr. Berwick Discovers Toxic Politics Too Late

Dr. Berwick listens to Ms. Sebelius
If you're interested in a post-mortem of Dr. Donald Berwick's failure to be confirmed as CMS Administrator, check out his November 13 JAMA article on "The Toxic Politics of Health Care." 

He identifies six causes of our national discontent, which the social media-minded Disease Management Care Blog has boiled down into 140 character or less tweetable summaries:

Money: there are too many entities making too much money to give up on the status quo. "Reducing costs" means cutting into someone's income.

Unorganized majority latent interests: the majority of Americans can't see or translate their interests into effective political action.

The Silence of Professions: Organized medicine has been all about the SGR and tort reform.  They should advocate for health reform.

Suspicion of Science: public trust in science is eroding because of its elitism. That, in turn, feeds into fear of rationing.

Duality of self interest: a lot of people work in the health care industry. Cutting costs will add to U.S. unemployment woes.

Ambivalence about Federalism: it's difficult to develop a coherent national health policy when power is shared with the states.

Ambivalence about the poor: it's difficult to convince the U.S. electorate that disadvantaged populations deserve public support.

For the record, the DMCB openly supported Dr. Berwick's nomination and still feels that he would have ably served his country as CMS Administrator.  That being said, one cause for his undoing was his failure identify these issues before he was forced to leave Administration. 

Docs like Dr. Berwick - and that includes the DMCB - unfortunately think that all they need are the facts to win the day. Not so: they need to address the money, catalyze coalitions, nudge stakeholders, reconcile multiple interests, cut deals and still do what's right.

He was the wrong guy at the wrong time.

The "Coporatization" of U.S. Health Care: Why the Good Prognosis for Health Insurers & ACOs May Be Guaranteed

Corporatization
The Disease Management Care Blog is ashamed to admit it, but it's reading Edward Klein's The Amateur. While much of the book is a conservative-partisan rehash of Mr. Obama's alleged personal and political shortcomings, it did raise one issue that intrigued the DMCB:

"Corporatization."   It seems this White House likes it.

As the DMCB understands it, this is a policy agenda that favors the formation of huge corporate organizations that dominate the national business climate. Its argument is that, thanks to their size and scope, these gigantic private, public and not-for profit corporations are better able to marshal the resources it takes to launch transformative programs, achieve efficiencies, take risks and make profits that are beyond the normal reach of traditional commerce. Think about the hundreds of billions-of-dollars-approaches to housing, financial services, battery operated cars, high speed rail, solar power, privatized space travel and, last but not least, health care insurance and delivery.

A key ingredient of corporatization is "partnering" with government in a way that blurs the line between private enterprise and the public interest. Ingredients include government-backed financing, special tax breaks, loans, grants, mixed Boards of Directors and sovereign investment funds.  The downsides are quite familiar also: crony capitalism and too-big-to-fail status 

The best example of corporatization is China. Beijing centrally orchestrates many of its key economic sectors including finance, banking, housing, public transportation and heavy industry with an opaque mix of public and private companies. While political reforms and respect for human rights have been found wanting, the prospect that China could eclipse the United States in the next 25 years has prompted many in the U.S. to admire China and reexamine the merits of old fashioned capitalism and unfettered markets. For an interesting example of that thinking, see this editorial by Andy Stern that recently appeared in the Wall Street Journal.

What could this explain and what are the implications?

1. The abandonment of the government-run "public option" early in the course of creating the Affordable Care Act. Despite his hostile anti-insurer rhetoric, Mr. Obama's ultimate belief in large mega-insurance corporations, a) regulations and b) public subsidies that bind the behemoth insurers to D.C. won the day.  And it ain't going away anytime soon.

2. The near ideological support by this Administration for Accountable Care Organizations. Despite little track record that ACOs offer a viable business model, the notion of large regional providers partnering with and led by CMS is fully consistent with a belief in corporatization.  This makes the DMCB wonder if Mr. Obama's intent is to assure that ACOs succeed, no matter what.

Pioneer ACO Program Results: Why Saving Money for CMS Doesn't Mean The Business Model is Viable

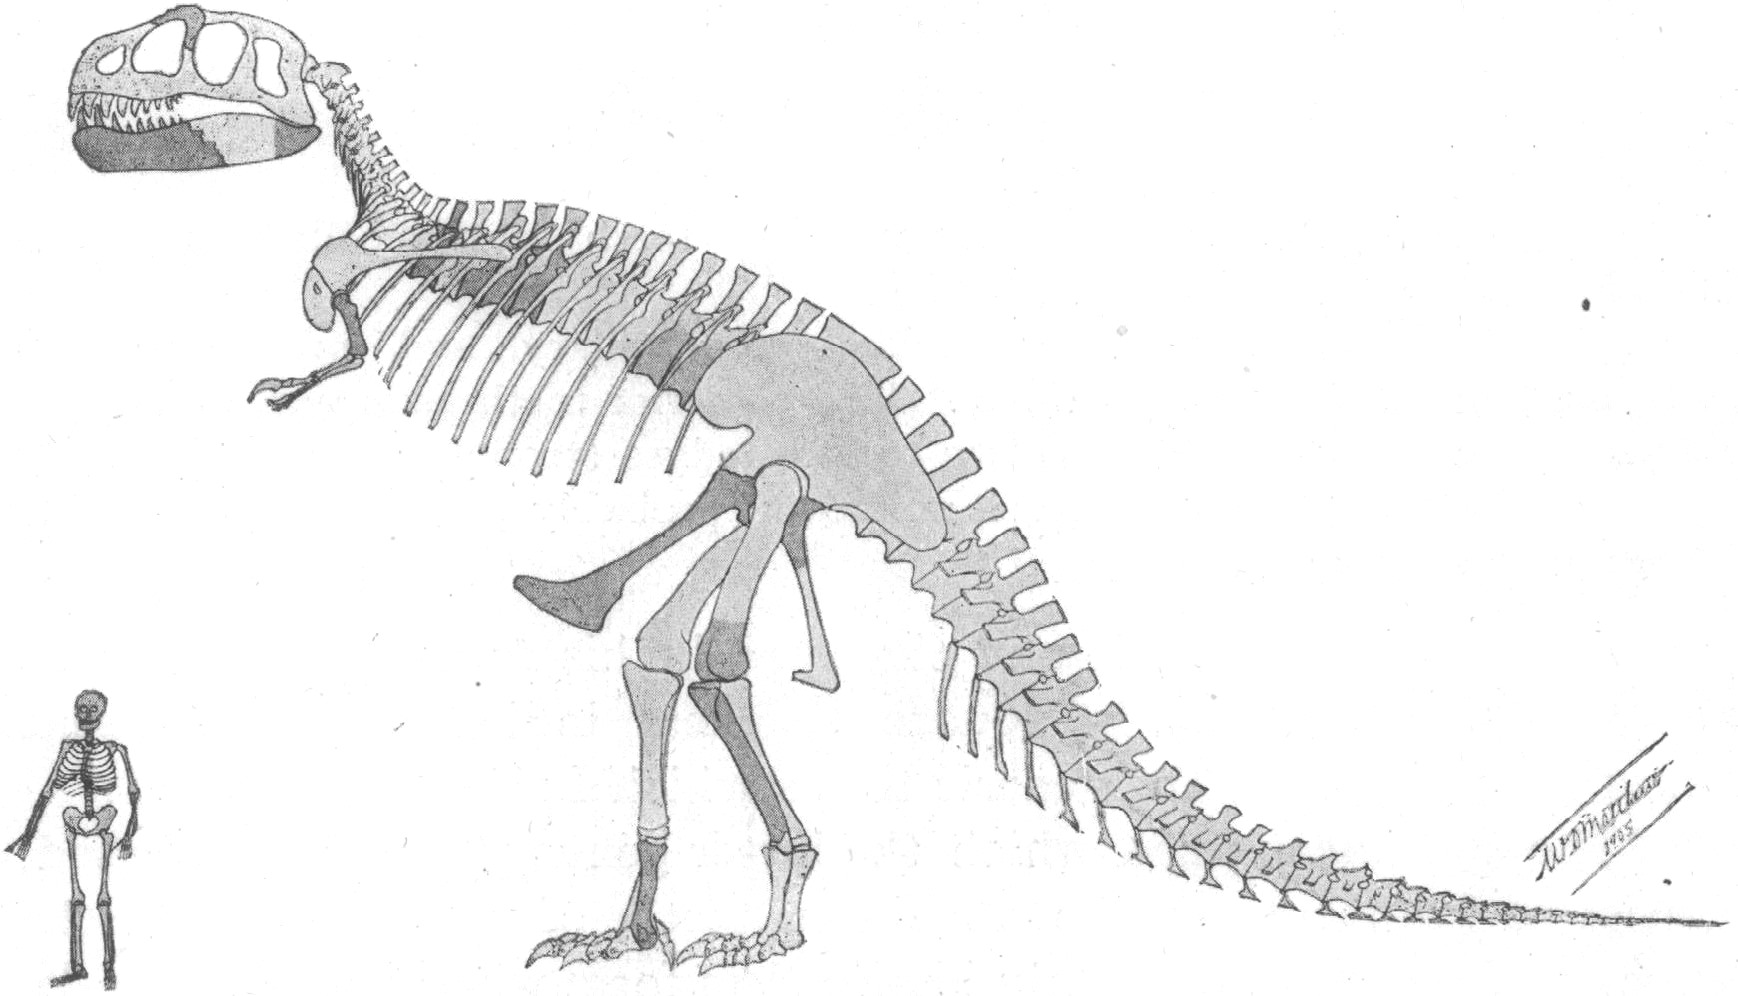
According to South Dakota researchers, the predator status of Tyrannosaurus rex can no longer be questioned. After finding one of its teeth embedded in the healed spine of a Hadrosaurus, paleontologists now believe T rex was a fearsome hunter, not an carrion munching opportunist. 

But, asks the Disease Management Care Blog, how do we really know that that Hadrosaurus wasn't  pretending to be dead when the T rex took its bite?  Alternatively, the Hadrosaurus could have been sleeping and only looked dead to a slow-witted and lazy T rex. 

Dino doubts, says the DMCB, remain.

Such is the level of skepticism that the DMCB is bringing to its reading of the recent CMS press release describing the initial results of the Pioneer ACO program.  CMS says "positive" and "promising." The DMCB says "problematic" wonders if, like the T rex dilemma, there isn't an alternative interpretation.

The DMCB explains.

Recall that the Pioneer ACO program is designed to test whether large integrated organizations can be successfully rewarded for reducing health care costs through a program of "shared savings."  Under the program, if the savings exceed a minimum threshold, CMS will remit a portion of the upside savings back to the participating organizations.

According to the press release, the health care costs for the 669,000 Medicare beneficiaries cared for by the 32 Pioneer ACO program providers grew only .3% versus .8% for a parallel group of "similar beneficiaries." 13 organizations exceeded the savings threshold, which will lead to Uncle Sam writing checks for $76 million in shared savings.

This front page article in The Wall Street Journal has more detail. It says 18 of the 32 reduced health care costs, which leads the DMCB to conclude that five otherwise "successful" participants did not cross the required savings threshold. Two participants lost money. That, in turn, suggests the remainder, or twelve, broke even.

Details on how each individual institution fared are not readily available.  According to WSJ, Boston's Partners Healthcare reduced Medicare claims expense by $14 million.  They will be rewarded with a shared savings check of $7 million. Wisconsin's Bellin-ThedaCare will get "several million."

Good "win-win" news for the Pioneer organizations, CMS, Uncle Sam and U.S. taxpayers, right? A critical mass (40%) achieved millions in shared savings, which means proof of concept met and that a key part of Obamacare is successful, right?

"Not exactly," says the DMCB.

It figures 100% of the participating organizations had to each invest millions for personnel and other infrastructure to pursue the Medicare savings in the first place.  In other words, they were in the red before Pioneer even began.  That means that, in addition to the two participating organizations that lost money, the 12 that "broke even" as well as the 5 that did not make threshold also lost millions. 

That's 19 losers or almost 60% of the participating organizations.

In addition, it's possible that for some of the 13 "winners" that the shared savings awards won't  match their up-front multi-million dollar investment either.  Assuming that's true, it's possible that as many as two thirds of the Pioneer organizations lost money. No wonder 9 of the participants have signaled a desire to exit the program.

The DMCB's dinosaur analogy may be apt.  Given a two out of three likelihood of losing millions in the first year of operations, ACOs may just be too big and complicated to survive in the current health care environment.  Nonetheless, the Pioneer program will continue and the DMCB will stay tuned for the Year 2 results.

In the meantime, the DMCB wishes CMS good luck in using these "positive" and "promising" results to expand the program anytime in the near - or distant - future.  

Discovering What We Don't' Know About Risk-Adjustment for Hospital Readmission Rates in Medicare

Something like this?
When the Population Health Blog agreed with the spouse that it was time to replace the living-room gas fireplace insert with something more sleek and modern, it then turned its attention to changing the surrounding mantle. The PHB favored something heraldic, featuring partially-garbed warrior babes, sporting shields and sandals. Cherubs too.  Preferably oak.

After some counseling from the PHB spouse, it came to realize that its wayward tastes in interior design may be a function of going sans helmet during its childhood bicycle riding, its deepening appreciation of bourbon's mysteries and pausing too frequently on Fox News' The Kelly Files. 

Naturally, the PHB wants to know the relative influence of each. Increasing exposure will help it propose some ideas for the unfinished basement.

Hospital administrators are dealing with a similar problem when it comes to readmissions.

Approximately 20% of discharged Medicare beneficiaries come back within 30 days. In response, CMS financially penalizes hospitals with high readmission rates for heart attack, heart failure and pneumonia. To reduce that penalty, hospitals have asked about the quality of their care, discharge planning and follow-up outpatient care. 

But, what is the relative impact of each? Where should administrators focus their corrective actions? 

Or, like the PHB and interior design, are readmissions ominously outside of anyone's control?

According to some interesting research, it turns out that more than half of the variation in readmissions may be outside of hospitals' control.  What's worse, CMS doesn't account for that in its calculation of the penalty that uses patient factors, such as age, gender and illness burden.

That's the conclusion of this recent article appearing in HSR Health Services Research.

Herrin and colleagues correlated CMS's Hospital Compare readmission data with each hospital county's socioeconomic data (rural vs. urban, persons living alone, employment status and educational level), access to care (the per capita density of primary care and specialist physicians as well as hospital beds) and nursing home number and quality (the number beds and the number of high-risk, long-term patients with bed sores).

Based on risk-adjusted rates from 4,079 hospitals in 2,254 counties, the authors found that more half of the variation in hospital readmissions was statistically explained by the counties' data.  That included persons living alone, low educational attainment, urban setting, a higher number of Medicare beneficiaries, fewer primary care physicians, fewer nursing home beds, higher numbers of nursing home patients with bed sores.  More beds and more specialist physicians were also independently associated with higher readmission rates.

The Population Health Blog's take?

As it noted previously, much of the vituperation around the unexplained variation in health care has been less a function of an inefficient health care system and more a function of our inability to identify the underlying drivers of utilization.

And now we're getting better. The HSR article shows that when it comes to readmissions, much of that variation is a reflection of the poverty in our neighbors' homes as well as the strength of the primary care network and the ability of nursing homes to act as a cushion.

Hopefully the mandarins at CMS will take these findings into account as they continue to financially sanction hospitals for readmissions. A more sophisticated approach to risk adjustment could help lessen the budgetary impact of county-level factors that are outside the hospital administrators' control. 

And since hospitals' bottom lines typically reflect the populations they serve, better risk adjustment could also lessen the disparate impact on the nation's poorest hospitals.

Image from Wikipedia

I'm From CMS and I'm Here to Help

Writing in JAMA "online first," CMS Administrator Tavenner and colleagues offer a payment reform "framework" that includes "multipayer collaboration."  The article is wonky, so the Population Health Blog dons its universal adminispeak translator so us normal humans can better understand what CMS is up to.

According to the writers, CMS has a history of innovatively implementing reforms that were later adapted by other insurers. The most famous example is the hospital "DRG" system that, starting in 1983, paid for a diagnosis in lieu of a daily room rate.  Suddenly, hospitals had an incentive to shorten hospital stays, which is precisely what happened in the years that followed.

Buoyed by this success, the authors describe the merits of championing Medicare's transition from "category 1" fee-for-service without any link to quality to "category 4" population-based payments that are linked to quality. And, as CMS embarks on this excellent payment journey toward accountable care, they'll get other commercial insurers to mirror their efforts by:

"Being conveners" as in "working with" other insurers in a region or a state to implement large payment reforms.  Working with may include grants;

"Incentivizing," as in requiring the participation of other payers prior to funding any large pilot programs.

"Working with states" to implement additional reforms, when the state has sufficient influence over the health insurance or delivery system.

The Population Health Blog's take:

"Category 4 population-based payments" are a form of capitation that are ultimately designed to transfer insurance risk from CMS to providers. The PHB hopes the bureaucrats at CMS are aware of the risk re-introducing some 1990s-style managed care abuses. 
 
What also goes unmentioned by the JAMA article are examples of CMS payment reform unintentionally gone awry, including RVUs, regional payment variation and the SGR with lingering fraud. While CMS has had its successes, it's also had more than its share of problems.  Time will tell which track record will apply to population-based payments.

Convening was an art developed by Medicaid programs.

Ms. Tavenner implies that population-based payments (a form of capitation) are intrinsically linked to quality.  Nothing could be further from the truth, since it's possible to reward quality while also relying on a FFS methodology. 

Accountable population-based care remains a large experiment.  Ms. Tavenner implies that there is an aura of inevitability.  The PHB learned long ago that the sign of a good plan is an exit strategy in case things go south.  The PHB didn't read that here.

The Dichotomy of Medicare’s Data Release Policy: Moral Suasion and the Limits of Mass Data Transparency

The Disease Management Care Blog continues to welcome blog posts from outside authors. This is another one courtesy of Erik Tollefson, who works in the health policy field. He can be reached at erikDOTmDOTtollefsonATgmailDOTcom.

Medicare has had an interesting few weeks: Not only did Congress manage to pass another one-year “fix”  to the (unsustainable) sustainable growth rate reimbursement scheme, but planned Medicare Advantage cuts magically turned into a marginal increase (at least for some insurers) after deftly applied political pressure. This behind-the-scene politicking set the stage for CMS’s second massive release of provider data last Wednesday. Although the data release may further codify extant evidence of some specialists being more richly compensated than their primary care colleagues, coupled with the potential pursuit of fraudulent claims, unfiltered transparency reveals Medicare’s weakness in providing useful transparency for beneficiaries. 

CMS formally released data detailing the 100 most common inpatient services, 30 most common outpatient services, and all physician and other supplier procedures and services performed on 11 more Medicare beneficiaries. The data included information on the doctor who performed the procedure, as well as the city and zip code where the procedure was performed. The biggest related take away seems to be a rather intuitive one: specialists, particularly cardiologists, ophthalmologists, and oncologists, are the biggest recipients of Medicare reimbursements: The three groups of specialists accounted for 7% or $5.6 billion of reimbursements in 2015.

Some in the medical community have responded to the perceived public scorched earth exercise circumspectly: hell hath no fury like scorned ophthalmologists. Valid questions, however, have emerged not only regarding the veracity of released data, but also the lack of context: some individual provider numbers may serve as a pass-through for entire practices, and a longitudinal release of data might allow for a more accurate picture of how service and drug utilization has changed as the country’s demographic profile has grown older. 

In response, CMS and politicians have responded that the benefits of “transparency” would likely drive more cost-effective care with less waste. Putting aside concerns of what transparency actually means in this context, an economist might ask a more apposite question: while the literature shows that public excoriation (in limited doses) may be effective in reducing price variance in an established legislative framework on the supply side, where are equivalent measures to empower consumer (demand–side) decision making?

To perhaps put a finer point on it: while variance in the pricing of procedures by hospitals and providers is certainly a problem, an equal problem is the variance in treatment across patients using non-cost effective treatments and medical devices that add little or no value to outcomes.  On this critical point, CMS and their data are silent. While further data releases may address this critical lacuna in consumer information, it is not likely: statute prevents the agency from making drug and procedure approval decisions explicitly based on costs.  Thus, an odd dichotomy has emerged in Medicare’s transparency campaign: exposure of the downstream cost equation (doctors), while leaving the curtain back on the furtive upstream costs including the RUC committee and other important input prices that would help consumers to make more informed decisions. 

The conflation of releasing big data with transparency is not a fatal error. Numerous useful data products may ultimately be developed as a result of CMS’s efforts.   A bigger problem, however, may be the asymmetrical use of moral suasion to expose doctors to the glare of public scrutiny without giving consumers information on the cost and outcomes related to technology and drugs use. If transparency does not result in more informed decision making, some would argue it is not transparency at all.

The Hospital Readmissions Reduction Program: Cautions and Caveats

"Maybe you should go
back to the hospital!"
Ask most wonks - especially ones who never took care of a patient - about "readmissions," and, after quoting this article, these health policy Urkels will tell you that returning to a hospital is the poster-child of all that ails U.S. medical care. Providers who can't get it right the first time, they say, are not only giving slipshod care, but are double dipping because their mistakes generate even more fat fees the second time around.

"Balderdash!" says the Disease Management Care Blog. Many Medicare inpatients are so sick that it's a miracle that they get to go home in the first place.  Keeping patients in the hospital can be more life-threatening than the home environment and, when things don't get well after a discharge, it's often more a function of social support than medical skill. 

That doesn't mean that CMS is going to listen to docs and back off of its Hospital Readmissions Reduction Program (HRRP). Using risk-adjusted actuarial projections, every U.S. hospital will be prone to a possible payment reduction if their observed rate of readmissions for heart attack, heart failure, and pneumonia exceeds the expected rate. Based on those projections, approximately two thirds of hospitals could be penalized.

Writing in the New England Journal of Medicine, Karen Joynt and Ashish Jha point out that hospitals are concerned because 1) readmissions fall outside of their control and 2) the actuarial projections are imperfect.  As a result, hospitals that care for the most fragile and socioeconomically disadvantaged are at risk for paying more than their fair share of CMS's $280 million claw-back penalty. 

The NEJM authors recommend three modifications to CMS' HRRP:

1. Include patients' socioeconomic status in any risk adjustment modeling. One easy-to-obtain modifier, for example, could be whether the patient is on Supplemental Security Income.  Patients on SSI are less able to cope, which is why they quality for the program in the first place.

2. Include hospitals' mortality rates in any risk adjustment modeling.  Hospitals with special expertise are less likely to have borderline patients die on their inpatient services, which means they'll have their more than their fair share of fragile survivors.

3. Limit the penalty to readmissions that occur within hours or days of a discharge, instead of the current problematic policy of counting any readmission that occurs within 30 days.  It makes sense to believe that a premature discharge or slipshod discharge planning is at fault if the patient returns within 3 days instead of three weeks.

Since it's unlikely that HRRP program is going away, the DMCB agrees with the three recommendations.  In the meantime, it also suggests:

1. CMS should be held accountable by Congress to execute well on the program,

2) Claims analytics - possibly using a "Big Data" approach - should be applied to Medicare claims to examine whether hospitals are turning to two potential options to undermine the program:

a) gaming the system by altering how they "code" the billing for their readmission patients, or

b) accepting the penalty because of favorable income from readmissions.

Image from Wikipedia

Of Medicare Shared Savings Program (MSSP) ACOs, Start-Up Costs, Preliminary Financials and Data Support

The Disease Management Care Blog didn't know there was a "National Association of ACOs" either, but they've just released results from a "web" survey of the organization member ACOs that are participating in the Medicare Shared Savings Program.  You can read more about the Program here. 

Of the total number of 123 MSSP participants, 35 anonymously participated in the survey. Their covered beneficiary numbers ranged from 5,100 to 78,000.

Among the findings:

Start up costs in the first year of operation averaged $2 million, with a range from $300,000 to $6.7 million.  With continued operations, the average cost over two years was $3.5 million. Total capital needs averaged $4 million.

While Medicare has yet to release any formal financial results, the ACOs' estimated results showed that 13 guessed they would break even. Nine will gain an average of $1.3 million and six will lose $1.3 million.  Six had no estimates, while other gains and losses ranged from positive $9 million to negative $10 million, respectively.

The biggest problem? "CMS data and learning to access it and process it."  This required pricey information technology with an average of $413,000 internal and $443,000 external costs.

The DMCB's take:

Running an integrated delivery system or physician-hospital organization as part of an ACO is a very expensive and capital intense enterprise.  Given the additional costs of new technology, electronic records and personnel, some of the ACOs may not be able to afford the loss of millions of dollars.  It remains to be seen how Medicare will handle the downside of hospital lay offs or clinical program discontinuations among some of the MSSP participants.  Will members of Congress have to get involved on behalf of their local constituents?  Stay tuned!

As the disease management industry learned, it's one thing to "save money," it's another to save money in excess of fees plus program costs.  $3.5 million over two years is a lot of money to make up before you break even, making the DMCB wonder if cheaper programs (such as population health management) with a more modest scope (such as reducing readmissions) may have a better long term value proposition. Once again, stay tuned.

And the Disease Management Care Blog predicted there'd be problems with the data feeds here.  Recall that one of the problems with the Medicare Health Support program were "execution" problems with the timely provision of utilization data from CMS.  ACOs - and the Medicare beneficiaries they're taking care of - deserve better. 

Health & Human Services Office of the Inspector General: EHRs Can Facilitate Medicare Fraud

EHR fraud police?
Disease Management Care Blog readers are well aware that it is a nattering nabob of electronic health record (EHR) negativity. It not only has the professional scars from past encounters with these on-screen scourges, the DMCB's literature reviews suggest the impact of the EHR on quality is questionable and its ability to reduce costs is illusory In fact, there's evidence that it can increase costs and hike hospitalization rates.

In addition, the DMCB has repeatedly raised the phenomena of copying and pasting and zombie diagnoses that lead to bloated and inaccurate EHR notes.

Well, readers and detractors no longer have to take just the DMCB's word for it. Things are so bad that even CMS should be worried.

According to this just-released report from the Department of Health and Human Services' (HHS) Office of the Inspector General (OIG), "copy-pasting" and "overdocumentation" are increasing the rates of Medicare fraud.

The former can pepper the EHR with inaccurate information that leads to unnecessary testing and treatment, while the latter makes the work of patient care appear more complicated than it really is.

What's more, the OIG points out that while HHS has been very active (and remuneratively generous) in promoting EHR "meaningful use," it has done little to respond to EHR-enabled fraud. Short of a live human personally comparing multiple notes simultaneously, CMS and its contractors have no ability to systematically audit patient billing records. What's more, there are no consistent internal policies in place or agreement on what to do even if it is detected (such as payment suspensions, overpayment adjustments or referrals to law enforcement).

The DMCB's take:

It remains to be seen if this warning will lead the HHS bureaucracy to catch up with another unintended consequence of health information technology.  If it does, the DMCB is worried that CMS may take its cue from the hostile RAC audits and further alienate physicians. 

Time will tell.

Image from Wikipedia
Leaderboard