Leaderboard
728x15
Showing posts with label Medicaid. Show all posts

Whither Obamacare, Now That "It's the Law of the Land?"


While a roll-back of Obamacare now is about as likely as spotting gargoyle statuettes among the DMCB spouse's holiday decor, a recent New England Journal article points out that the Affordable Care Act (ACA) - even if it is the law of the land - still has a very bumpy road ahead.

That's because of four key issues:

1. The States can still knot things up by forcing Washington DC to run the Health Insurance Exchanges (HIEs).  It's very possible that Uncle Sam won't pull them off on time and, what's more, there's a credible Supreme Court challenge looming over Obamacare's potential lapse in extending tax credits to the federally-run HIEs.

2. States can refuse the Medicaid expansion. While their statewide hospital associations are very  unhappy about that, Governors are either ideologically opposed or just plain wary of additional downstream costs. This could result in additional millions of uninsured, especially in the conservative "red" states.

3. Health care cost inflation is likely continue its upward spiral.  Congress, no matter how CMS' payment innovations turn out and no matter how much it wants to curtail costs, is unlikely to withstand the lobbying from all corners of medical-industrial complex involving thousands of pages of rules and regulations.

4. Deep public ambivalence about the law will continue. That means that as Congress and the President look for ways to control the Federal deficit, Obamacare is especially vulnerable. Unlike Social Security or Medicare, the ACA's "patchwork" of insurance reforms is headed toward the fiscal cliff without a strong supportive constituency. Before Congress even touches Medicare, it's far more likely to cut Obamacare. The first hit could be those insurance tax subsidies mentioned above.

A Brainy Health Wonk Review on Health Reform, the Affordable Care Act and Lots More!

Welcome to the Disease Management Care Blog, your host for this edition of the Health Wonk Review. This is a linked summary of the latest and best postings from an informal community of health policy bloggers with informed insights that readers, business leaders, academics and policymakers won't find anywhere else. We invite you to sit back, get a beverage, enjoy a snack and feed your brain as you join thousands of your colleagues and competitors in gaining a deeper understanding of the U.S. health care system.

When when when (of a miscellaneous nature)

When researchers act like politicians: The falsification, fabrication and plagiarism that comprises research misconduct is the topic of a post by Donald Kornfled over at the delightfully named Wing of Zock. Causes include the fear of failure, perfectionism, ethical lapses, grandiosity and psychopathy. Dr. Kornfield reviews potential fixes, including training courses, better mentorship with monitoring and protections for whistleblowers.

When for-profits run amok: Roy Poses at Health Care Renewal scrutinizes one health care system's latest branding campaign and acquisitions, pointing out that the lack of any specificity seems to confirm that this is all about profits, not patients; commoditization, not caring; and corporatization, not community.  Unfortunately, this is not an isolated incident.  You've been warned.

When outcomes are based on flawed research: David Williams of the Health Business Blog asks Al Lewis why no one believes the numbers that underlie the reported effectiveness of population health management, the medical home and wellness. It's easy, says Al: the math has been unnecessarily complicated, actuaries make mistakes and there's selection bias, regression to the mean, confounders. pressure to show success and, most of all, a widespread and regrettable under-recognition of Al's vast expertise.

No Health Wonk Review is Complete Without the Affordable Care Act

Will it never end? If you're interested in even more obscure legal theorizing over the constitutional legitimacy of the Affordable Care Act, then head on over to the Health Affairs Blog. It appears the ACA may only authorize consumer subsidy tax credits in "state" run exchanges. The failure to include federal exchanges in the legislation could be a pesky wording oversight (argued here by Timothy Jost) that is overcome by a common sense understanding of Congress' original intent, or a craftily worded way of giving the states one more incentive to open their own exchanges (argued here by Michael Canon and Jonathan Adler) that could backfire and conveniently hobble the roll-out of the exchanges.

If you had to pick one good thing about the ACA, would this be it? Have you heard about the ACA's insurance co-ops? Think of these as smaller regional not-for-profit health insurance plans that are sponsored by consumer-based organizations. Jay of the Colorado Health Insurance Insider describes how, thanks to a loan from Uncle Sam, a new rural co-op is being launched in Colorado. It plans to open its doors in 2015 with a target of 10,000 enrollees.

And if you wanted to convince skeptical voters about the rest of the ACA, Anthony Wright of the Health Access Blog reminds us that the Brits proudly featured their National Health Service (NHS) in the Olympic Opening Ceremony for lots of good reasons.  The conservative DMCB not only wonders what marketing lessons CMS can learn from this (hint: opening ceremony at the World Series) but it has had its wacky closet Tea Party fears confirmed: "ACA" spelled backwards is "NHS" and its Maximum Kommissar will be First Citizen Don Berwick.

Massachusets reminds of what could follow the ACA: David Harlow of the HealthBlawg looks at what the Bay State is doing now that Romneycare's reforms neglected to tame health care cost inflation: Regulations that prohibit excessive provider price increases,promotion of the medical home and ACOs, greater market transparency, more public financing and physician liability reforms.

And what do the brokers think of the ACA? Hank Stern of the InsureBlog describes a blow back on the insurance provision that excess administrative costs must be rebated back to the beneficiaries.  Not only is it very burdensome to calculate in group policies with individual underwriting, but the tax implications are best considered in a "Michelob teaching moment" (that'll make more sense when you read the entire post, but trust the DMCB: it's not good).

Accountable Care Organizations?  Amazingly, only one HWR submission!

Is the DMCB really a DmCB?  DMCb?  Kerry Willis of the Health Talent Transformation blog calls on docs to resist the siren call of the ACOs' easy money. Look closely, he says, and you'll notice a strong resemblance the 1990s-style PHOs that were long on hospitals' interests and short on physicians' needs. He suggests that a better name would have been pHO. That's why he says unless ACOs use the physician-led patient centered medical home or concierge practices, a better name for them would be AcO.

Of Budgets, Priorities (and their evil architects)

In the taxpayers-get-what-they-pay-for-department, Liz Borkowsi of ScienceBlogs reviews a Health Affairs study on physicians' willingness to care for coming wave of new Medicaid beneficiaries. Based on a representative sample of docs, 69% are currently accepting such patients, but the numbers vary by geography (the rate is only 40% in New Jersey, for example).  The researchers estimate increasing payment rates to match Medicare's fee schedule would likely increase acceptance by an average of 10 points. One solution is expanding the nation's 8000 community health centers with the $11 billion allocated by the ACA. Unfortunately, that money has been a tempting target for budget-deficit minded politicians.

...and here's more on the taxpayers-get what-they-pay-for: Jason Shafrin of the Healthcare Economist blog looks at Medicare's reimbursement for for Alaskan physicians and finds evidence that new and established Medicare beneficiaries are having trouble finding a primary care physician. It seems the physicians would rather fill their clinics with better paying commercially insured patients.  If that income stream ever gets cut off, thinks the DMCB, the docs could always turn to the remunerative world of blogging.

How about what patients don't want to pay for? Medical student Justin Jones examines end-of-life care and finds doctors who forgo aggressive treatment of their incurable cancers may be role models for the rest of us.  Yet, despite some compelling anecdotes and the disdain for death panels and cost considerations, the provocative DMCB still wonders how insurers and their risk-bearing providers will reconcile an obvious conflict of interest over death with dignity and reducing claims expense with upside gain sharing.

In the physicians get annoyed-on-how-they're-monitored department, everyone agrees we need to measure health care quality and make providers more accountable.  Unfortunately, making that happen in the real world is proving difficult. Brad Flansbaum of the Hospitalist Leader blog offers a quick primer on CMS' early efforts at physician report cards in Kansas, Iowa, Missouri and Nebraska and explores the pros and cons of measurement at the individual, group or hospital level.

Tough Choices: Chris Langston, the Program Director at the John A Hartford Foundation blog points out that the dysfunctional economics of Medicare and Medicaid are ethically troubling. Decreased payments for geriatric services are part of a troubling pattern of discriminating against the poor and elderly. He asks if it's time to recast the political debate over the current scope of government insurance as a beneficiary rights issue.

I knew it! Is Republican VP candidate Paul Ryan a real budget hawk, or is his record in Congress marred by the realpolitik of partisanship and party loyalty? Joe Paduda finds compelling evidence of the latter.

Want more dirt on Paul Ryan? Harold Pollack over at healthinsurance.org says he's "extreme," a "pampered millionaire known to purchase $350 wine" with proposals "opposed by huge middle class constituencies" that would lead "between 14 and 27 million low-income Americans to lose health coverage" and cause "deep" cuts in highway repair, K-12 education, environmental protection, public health and law enforcement."

Heroes vs. affordability: While the U.S. military has increased the visibility of post traumatic stress disorder (PTSD), Lynch Ryan of Workers Comp Insider blog reminds us that our nation's police force members are not immune. Cops are far more likely to die by their own hand than be killed in the line of duty, and their rate of suicide per 100,000 matches the U.S. army. Lynch explores the workman's compensation implications: should treatment of the disabling stress of witnessing violence be covered, or is this part of the job?

Your next host for the Health Wonk Review will be Louise Norris of the Colorado Health Insurance Insider Blog.

The Italics and Dot-Dot-Dot Edition of the Cavalcade of Risk

Welcome to your latest edition of the Cavalcade of Risk.  The Population Health Blog is pleased to offer this linked summary of some of the best and latest bloggery dealing with economic risk.

Knowing how busy readers are, this particular edition wanted to focus on the "bottom line" of each entry. The most important insight is at the end of each paragraph.....

Enjoy!

Auto

Wondering if that non-performing capital assessment called a "parked car" can be addressed by "peer-to-peer car sharing?'  Well, if you think you can grab a portion of Hertz's market share by renting that car, you may want to pause and think about what your automobile insurance has to say about it.  Hank Stern over at the Insure Blog points out that a wreck may not be covered leaving you personally responsible for another party's injuries....

Workers Comp

Did you know that employers can be arbitrary, hostile and vindictive?  That employees can be sullen, suspicious and uncooperative?  Toss in a significant  job injury, and you've got is what AMAXX Blog writer Michael Stack describes as an unwritten part of a workers compensation adjuster's job description: being a peacemaker. Employees ultimately do better if they get to work sooner rather than later, and bosses do better they step back and let the workers comp adjuster deal with any possibility of malingering....

Data Privacy

After Target and eBay, your company's (or, come to think about it, government's) databases may not only be next, that possibility is greater than you realize.  RJ Weiss at the Weiss Insurance Agencies does readers a service by summarizing some of the numbers around the risk of data breaches, including a cost of $195 to $246 per record, an average loss of 2.8% of customers and that having strong preventive measures in place can reduce your cost by $8.98 per record.  Important sources of break-ins include those portable devices and sloppy third parties....

Health Insurance

We'd all like to think that hospitals are working hard to reduce costs and increase quality thanks to the government's value-based purchasing initiative.  Jason Shafrin of the Healthcare Economist summarizes a recent peer-reviewed publication on the topic and the bottom line answer is "not exactly." While results may be more a function of the baseline that was used, there was no discernible impact on clinical process or patient experience performance for Medicare beneficiaries....

Speaking of payment initiatives, your host's Population Health Blog (PHB) takes a look at another recent scientific publication that examines how a statewide bundled payment program stumbled.  The process was stymied by the usual payer-provider tensions, inadequate information technology, regulatory concerns and difficulties on defining just what makes up an "episode of care." It turns out that getting bundled payment off the ground is far harder than it looks.... 

Getting health insurance between jobs should be easy, but it's not. Louise over the Colorado Health Insurance Insider cuts through the noise of Obamacare and the individual market by offering up some useful insights, including the definition of a "qualifying event," the 60-day rule and the option of using Medicaid to trigger a qualifying event to navigate the 60-day rule....

The next host of the Cavalcade of Risk is Paul Dzielinski.  The PHB is looking forward to his hosting debut!

Medicaid Is Better Than Nothing

That's the DMCB conclusion after reading this hot-off-the-presses New England Journal article on Mortality and Access to Care among Adults after State Medicaid Expansions.

Three states (Maine, Arizona and New York) in the 2000-2005 time frame increased Medicaid eligibility to mostly include childless adults meeting a variety of poverty thresholds.  The authors compared changes ("pre-post") in publicly available death rates and health status statistics in these "intervention" states to neighboring states that acted as quasi-experimental "controls (New Hampshire for Maine, Nevada and New Mexico for Arizona and Pennsylvania for New York).

Over time, new Medicaid enrollees were slightly older (40.6 years vs. the average of 40 years), more likely to be male (57% vs. 49% in the general population), nonwhite (27% vs. 20%) and in fair or poor health (20% vs. 11%).

What was interesting was that the authors compared the county-level changes in mortality for the entire state population, not just Medicaid enrollees.  Using standard statistical methods to account for baseline differences, the authors found that adjusted all-cause mortality for the intervention states declined by 19.6 per 100,000 versus the control states.  Since it takes time for Medicaid enrollment to actually increase after a change in eligibility, the authors also examined the impact over time. They found a strong statistically significant correlation between growing Medicaid enrollment and mortality.

Medicaid expansion was also associated with decreases in rates of patient surveys showing that there was "delayed care" and increases in self-reported excellent or good health status.

The obvious conclusion of the study was that expanding Medicaid eligibility allows persons who are otherwise without insurance to access the health system and receive care for conditions that would otherwise kill them. The DMCB finds the results convincing and should inform the debate in some states about the life-saving merits of expanding Medicaid.

Critics could quibble that unknown factors not captured by the study could have accounted for the observed differences (did pumping more Medicaid money into the system enrich hospitals, enabling them to provide a higher level of care?) and that association does not prove causality (could booming state economies lead to a healthier population, while a generous Medicaid expansion had nothing to do with it?).

DMCB questions:

1) This study doesn't compare Medicaid insurance vs. commercial insurance.  If there were a way to use the commercial markets (for example, vouchers), would patients far better?  There is research that suggests the answer could be yes.

2. A cruel but important question: how much did it cost?  Expanding Medicaid did not save money, it cost and it would be interesting to know the cost per person, per person-year or per quality adjusted life year.

Governors Need to Do the Right Thing for Medicaid, Even If It's for the Wrong Reasons

From time to time the Disease Management Care Blog receives submissions from readers. M'Lynda Owens is a registered nurse with a research interest in population health as well as the provider and payer dimensions of the Medicaid program.

So now several States (Texas, Florida, Mississippi, Louisiana and South Carolina) are exercising their constitutional right, affirmed by U.S. Supreme Court, to opt out of expanding Medicaid to uninsured persons meeting federal poverty guidelines. Their rationale is that they cannot afford the increased costs of an “unfunded mandate” that will accrue once the federal match is reduced to 90%. These five states account for approximately 20% of the population of working poor who would otherwise be eligible for health insurance coverage under the ACA.

Governing.com has posted an interactive state-by-state analysis of the expected impact of ACA. It’s worth taking a look at the map. The number of uninsured in these states ranges from just over 500,000 to 5.8 million, while the percentage of potentially eligible uninsureds ranges from 43% to 63%.

Since many of the states that are opposing an expansion of Medicaid also have the high rates of poverty, obesity, diabetes, and uninsured adults, how could anyone is it believe that this decision is in the public interest? The likely outcome of this venal "opt-out" decision is that all the citizens of these states will have to bear an even greater portion of the burden of the states' responsibility for the working poor, but not in a straightforward fashion. Rather, this burden will take the form of hidden taxes and additional strains on public wellbeing in other sectors such as infrastructure.

The good news is that the uninsured appear to have a strong ally in their states' hospitals. Uncompensated care cost hospitals nationwide a combined $39.1 billion in 2009, according to estimates from the American Hospital Association. According to the website, governing.com, the Texas Hospital Association worries that its members will be forced to pick up the tab for those lacking insurance. One spokesperson stated “Texas hospitals recognize there are concerns with expanding the Medicaid population, but given the state’s high number of uninsured, all options for gaining insurance coverage must be closely considered.” He also said “Without the Medicaid expansion, many will remain uninsured, shifting costs to the insured and increasing uncompensated care to health-care providers.”

These states' governors likely expect that their ongoing attempts to disenfranchise the working poor will be politically popular with voters in the upcoming fall elections. It will be interesting to watch whether the hospitals and their allies, the physicians, will prevail and convince their states' politicians to opt into the Medicaid program and take the money.

If that happens, it'll be because the Governors were persuaded to make the right decision for the wrong reasons.

The Two-Sided Iron Triangle of Cost and Access and What It Means for Health Reform in 2015

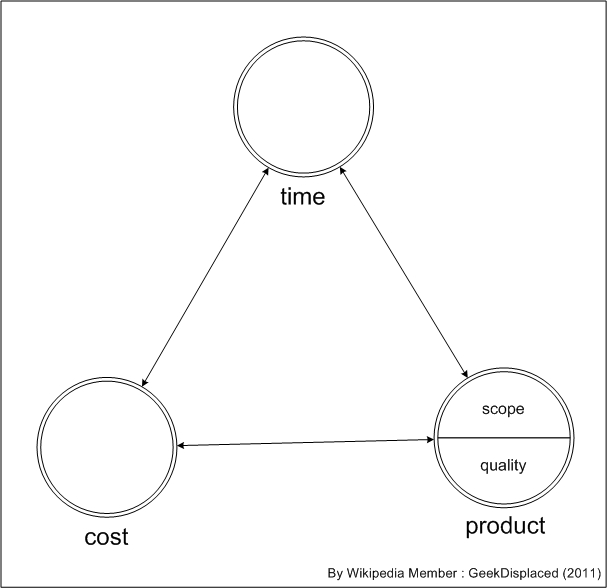
From time to time, the Population Health Blog likes to refer to this article on the "iron triangle" of health care reform. Using classic project management theory, it suggests health care planning is:

a) bound by 1) cost, 2) quality and 3) access, and

b) if there are limited resources, health system planners can only optimize two out of three.

Want to decrease costs?  Either quality will go down or access to care will decline. 

Want to increase access?  Docs and operating rooms will spend less time with patients (quality will suffer) or costs will go up, because you have to hire more docs or build more operating rooms.

Suppose you want to increase quality?  Because most interventions that increase quality are not free, it'll cost you.  Alternatively, fixed budgets and resources will have to be tasked to additional needs, so access will suffer.

It's admittedly simplistic, but this framework can be used even by the amateurs in the White House to better define the Veteran Affairs scandal. As the PHB understands it, VA administrators wanted to increase quality (more primary care, better mental health services), but they didn't have the budget to match it. Access declined and, voila, waiting lists developed.

Which brings the PHB to the insurers' dilemma.  The generous narrative is that commercial and government insurers can leverage "quality" and somehow increase access for more persons with insurance and/or "bend the curve" of cost inflation.  The "iron triangle" says that's not true and the PHB agrees.

That's because:

1) while it's possible to statistically assess outcomes in primary care settings, there is a shortage of primary care providers.

2) it's far more difficult to statistically assess outcomes in specialty settings, where there are limited numbers of patients, fewer commonly accepted outcomes and a greater impact of patient variation.

In other words, quality is neutralized. That means health care is a two sided triangle.

Assuming quality is now constant, the PHB now has another reason to predict that insurers will have only two options in 2015:

1) increase access to care for more persons, but that means increasing, not decreasing costs. That means higher out-of-pocket costs for patients, or lower reimbursement for providers.

2) lower costs, but that means decreased access to care. Providers will refuse to contract or more restricted provider networks be created.

Image from Wikipedia

A Thursday Three-fer: Diabetes Predictive Modeling, The Threat of Ambulatory Care Write Offs and It's the National Debt, Stupid!

At Risk?
Diabetes Predictive Modeling: Evidence Based, Peer Reviewed and Open Domain:

As Accountable Care Organizations, Patient Centered Medical Homes, care management vendors and managed care organizations continue to grapple with health care costs, they want to know who is at greatest risk in the coming months.  When it comes to diabetes mellitus, John McAna and colleagues (one of whom is the Disease Management Care Blog) is riding to the rescue with their American Journal of Managed Care paper "A Predictive Model of Hospitalization Risk Among Disabled Medicaid Enrollees." 

While the data were based on two states' Medicaid claims data sets, the research may be generalizable to other populations.  Factors that most strongly predicted a future hospitalization were increasing age (especially more than 65 years), a prior pattern of repeated hospitalizations (especially 3 or more) and the Charlson Comorbidity Index. The good news is that all the independent variables and their odds ratios are not-only evidence based, they're available for use by your actuaries and statisticians as quick as you can download the paper (after signing in) at the bottom of page 4.

Rumored Ambulatory Care Write-Offs: An Achilles Heel of Integrated Delivery Systems and ACOs?

In its recent travels, the DMCB was informed by two credible and astute physician-leaders that hospitals that have recently acquired outpatient physician practices are typically "writing off" ambulatory care bills because a) contesting small fee disputes are relatively costly and b) the threat of Medicare "overcharge" or RAC audits is existential.  That's significant because those small charges add up into millions and can mean the difference between a profitable outpatient clinic system and a loss leader.

It's Not the Economy, It's Not the GDP, It's the National Debt, Stupid:

The DMCB also recalls repeatedly hearing that it was President Nixon who first called attention to the growing fraction of the nation's gross domestic product going toward health care. The problem was that no one knew what was the "right" percent of GDP.  Mr. Nixon thought 7% was too high. If 7% isn't, in retrospect, bad, why is the current level of about 18% so bad?  What's so different?

The answer: it really is different this time.  What's bad is that health care is responsible for the lion's share of the separate problem of the growing national debt, which has been directly linked to national security.  Yikes.

The Oregon Medicaid Experiment: Good Study, Bad Politics

Examining the Oregon Medicaid Study
By now, most Disease Management Care Blog readers have probably read or heard about the release of the health and costs outcomes data from the Oregon Medicaid experiment. The purpose of the study was to ascertain whether one of the arguments still being used to support the Affordable Care Act is really true, i.e. that health insurance leads to better health leads to lower health care costs.

It's not a minor argument. When the important provisions of the ACA go "live" in 2015, liberal-progressive supporters of the ACA will be tenaciously seeking to validate the merits of health care reform, while conservative critics will be looking for any excuse to strangle Obamacare in its crib.

So naturally, if a well performed study supported or contradicted the health insurance hypothesis, it would make little political difference.

How was the study done?

Unable to afford universal enrollment of approximately 30,000 eligible persons into Medicaid, Oregon figured the only fair way to administer the program was to have a lottery. Because participating individuals were allocated to one of two options (with or without Medicaid) by chance, Oregon's approach had all the makings of a prospective randomized clinical trial.

The lottery was conducted in 2008 and the health status and health care costs for the winners and losers were compared using face-to-face interviews an average of 25 months later. While the lottery was state-wide, the study itself was limited to the Portland area. The researchers planned to compare the health status of 10,405 individuals who had won the lottery to 10,340 individuals who had lost and were not enrolled in Medicaid.

Not all persons signed up for Medicaid and others couldn't be tracked down for the one-on-one interviews, leaving a final number of 6487 (62% of the eligible) lottery "winners" versus 5842 (57% of the eligible) "losers."

What were the results?

All in all, the results were disappointing for persons believing the health insurance hypothesis. Having Medicaid didn't lead to better control of high blood pressure, diabetes, blood cholesterol levels or overall cardiac risk. There was also no impact on the likelihood of being admitted to a hospital or having to go to an emergency room.

The good news was that having Medicaid seemed to lessen the likelihood of battling untreated clinical depression and, if pap smears and prostate specific antigen tests are markers for access to primary care services, Medicaid increased that also. Last but not least, Medicaid participants were less likely to have catastrophic medical expenses or be in debt to cover medical bills.

Was the study perfect?

Nope. The study's generalizability was limited by being restricted to persons age 19-65 years in Medicaid and in an urban environment. Two years may not be long enough to truly gauge the benefits of having insurance. Many persons were lost to follow-up. Statistics limited the ability of the researchers to spot smaller improvements in health status.

And how did supporters and detractors of Obamacare react?

As expected. If bloggers are a window into the soul of the body politic, this KHN article amply demonstrates that no one's mind has been changed. Between inflating or minimizing the study's imperfections, cherry picking the outcomes and spinning them, we are no closer to achieving any consensus.

The Disease Management Care Blog's take:

Studies like the Oregon Medicaid study are not only rare, they're as good as we're going to get. Since no study is perfect, the likelihood that Washington DC will be able to use any nuanced research insights to inform the next steps in pursuit of the Triple Aim is not good.

The battle lines have hardened.

Controlling Health Care Costs: Different Countries, Same Levers

The levers that control health care costs
Ask an average voter how health insurers reduce costs and, thanks to years of hostile anti-insurer rhetoric, he or she will tell you that they "deny."  Think of it as "deny2" for both the person (who is no longer insured) as well as the procedure (which is "not covered"). 

Sophisticated Disease Management Care Blog readers know better. "Deny" stories are mostly anecdotal and that kind of misbehavior is largely prohibited. 

If insurers want to save money, there are far smarter ways to do it.  The same is true for government sponsored insurance.

After reading this Health Affairs article, the DMCB discovered that Canada, France Germany and England are using those smarter ways.

And so is the United States government.

How's that you ask?

While health care costs in other developed countries are lower than the United States, the contrarian DMCB has pointed out that today's costs are not all that important. A far more ominous trend is the rate of growth, a.k.a. "trend."  Year-after-year increases in health costs that outstrip GDP are far more threatening to governments' fiscal health, especially when budgets are being strained by other priorities, like combating terrorism, keeping tax-dodging French movie stars from moving to Belgium and helping Mr. Bieber retrieve his pet monkey from Germany.

So what are Canada, France, Germany and England doing to control health care costs?  According to the DMCB's read of Mark Stabile and colleagues' article, they are using three strategies:

1. Budget shifting: This involves individual beneficiary cost-sharing, as well as cost-shifting to private insurers and/or local governments. Ottawa, Paris, Berlin and London are also eliminating coverage of "low-value" services, devices or drugs. Yet, since backing away from universal coverage is out of the question, the central governments are also providing funding that protects low income individuals from otherwise unaffordable out-of-pocket costs.  While they're at it, coverage for "high value" services such as hospice, immunizations, dementia care (Germany) and hypertension care (France) is being expanded.

2. Budget setting: While England and France use national caps (that are flexible and subject to adjustments), all four countries have a growing reliance on regional or local price fixing as well as capitated payment arrangements. Pay-for-performance is being substituted for otherwise routine budget increases and consumers are being given their their own fixed personal spending accounts.  This helps limit the likelihood of future budget increases. 

3. Direct controls of health care supply: examples of this include cutting the number of hospital beds, eliminating coverage of certain drugs, increasing the number of primary care providers, using health technology assessment and relying on practice guidelines.

If this sounds familiar, it should.  As the DMCB noted here, the Feds are reducing Medicare's risk exposure by asking individual beneficiaries, providers and State governments to take on a greater share of health care costs.  They're also imposing budget controls by capitating providers with bundled payment and risk contracting arrangements. Last, but not least, they're controlling the supply of health care services by, for example, increasing payments to incent the adoption of electronic records and increase the pool of primary care providers.

It turns out rising health care costs are a global problem with the same set of policy options.

A February Edition of the Health Wonk Review: Insightful Nuggets From the Best Health Policy Blogs

A valuable nugget & more on the way
Welcome to the Disease Management Care Blog's hosting of the Feb. 28 Health Wonk Review.

This HWR is a summarized compendium of submitted posts by the smartest health policy bloggers in the known universe.  The DMCB assures you that you're in for a special treat because you'll find some insightful nuggets that generally go unseen in the mainstream media and academic literature.

When it's not mining the HWR for information, the DMCB combines acumen, skepticism, modesty, peer-reviewed science and occasional humor about health policy, care coordination, population health management as well as primary care, the medical home, health insurance and the electronic record.

It's so glad you stopped by.

The DMCB has organized the posts by topic: Obamacare's key reforms, various health economists' latest divinations on health care costs, hospitals, Medicaid, the internet, California, medical education and some British humor.  The quotes that head each section should give you a hint about what you're in for.

“This is a big f—-ing deal.” – Vice President Joe Biden

What's to Know About the Go-Go Growth of ACOs?

Lots, thanks to this Health Affairs Blog post by Leavitt Partners' David Muhlestein. He counts 428 accountable care organizations (ACOs). While all eyes are on the Medicare versions, it turns out the private sector has been on a less visible parallel track with "full or partial capitation models, bundled payments, retainer agreements, in-kind services and subsidies provided by payers, and pay-for-performance incentives." Did you know that most ACOs are in the West Coast and Northeast, or that there's an even split between physician and hospital-led sponsors? Mr. Muhlestein also points out that 2015 will be the year that we'll get to see some early ACO data. David and the DMCB will be watching very carefully and, if we report Medicare's outcomes are less than expected, the DMCB is looking forward to getting a "you'll regret it" email from somewhere in the Administration.

What's to Love About the Individual Insurance Market?

Could be lots, says Nicole Fisher of Wright on Health. She wonders if there is a silver lining in the growing evidence that some employers will drop their sponsored health insurance benefit and force their workforce into the individual market. That may force the individual market to have better transparency, less discriminatory underwriting, more choice and increased competition. As result, costs could be lower than expected, consumers will better understand the true costs of health care and portability could paradoxically improve. If things go really well, we could see a self-reinforcing cycle of market demand. And, wonders the DMCB, long lines outside doctors' offices.

Maybe, But What's NOT to Love About the Individual Insurance Market?

Louise of the Colorado Health Insurance Insider blog worries that persons who aren't poor but who are also not wealthy are in for some bad news if they believe that the reformed individual market will translate into affordable health insurance.  Unlike today's market, individuals will be less able to trade lower premiums for HSAs, high deductibles and (for persons over 30 years of age) catastrophic coverage. While minimum coverage requirements are a good idea, Louise says they're also expensive. She suggests it would be good public policy to flexibly accommodate a demand for higher deductibles and lower premiums.

An economic forecaster is like a cross-eyed javelin thrower: they don't win many accuracy contests, but they keep the crowd's attention - Anonymous

Persistent Partisan Perfidy on the ACA's Costs

Maggie Mahar, over at healthinsurance.org, indicts the latest libel against Obamacare.  Her ire is directed at those repugnant conservative pundits who should have known better than to glom onto an ill-considered U.S. Internal Revenue Service document about 2016's health insurance costs. Beware, says Maggie, no one really knows what costs will be in 2016. The DMCB is shocked, shocked that economists' and actuaries' inaccurate predictions are being intentionally misinterpreted for political gain.

Numbers With A Lot of Zeros

Speaking of economists, The Hospitalist Leader has compiled a linked list of peer-reviewed references that estimates the health care costs for the big name medical conditions. He senses that there's something amiss, because adding them up is much like finding Italy's olive oil exports far exceeds that country's domestic production. He thinks science writers, patient advocates, policymakers and yes, us bloggers, should promote better numeracy and, for starters, contrast any absolute dollar figures with helpful comparisons. That's why the DMCB is pleased to post this short instructional video on some math basics courtesy of the health insurance professionals who staff the IRS:


100% Coverage of Screening Services Is Not Good Enough?

Guess what?  When health care consumers are thinking about the cost of undergoing screening for a disease, they're also thinking about the next steps if disease is found.  Quoting a study in the Journal of Health Economics, Jason Shafrin of Healthcare Economist points out that zero dollar coverage for services - while noble - will have less of an impact than anticipated unless it's linked to meaningful coverage of treatment of the underlying condition.  In other words, health screening subsidies are not enough to maximize consumer buy-in.  No wonder the DMCB spouse is unfooled by offers to screen some sales prices for a jumbotron-sized flat screen for the living room!

"Phlegm free zone" - Sign seen at a local hospital

The Riddle of Readmissions

In this posted podcast (here), David Williams asks the Robert Wood Johnson Foundation's Anne Weiss about the recent depressing report on hospital readmissions.  Based on 2010 Medicare numbers, it doesn't look like the national rate has gone down all that much and that the considerable variation between different areas of the country remains.  David and his guest also chat about some promising best practices that being used in some settings to reduce readmissions, what patients and their families can do about lowering the likelihood of a readmission and whether the practice style of hospitalists is part of the problem or a potential solution.  Despite evidence that population management can reduce readmissions, Ms. Weiss rejects for-profit vendor participation, believing that hospitals should be happy to hire more personnel in lieu of partnering.  Let the "build or buy" games continue, says the DMCB.

"Governor Brown's budget plan also counts on $488.4 million in savings from a 10% cut to Medi-Cal reimbursements. Medi-Cal is California's Medicaid program." 1/30/13 News Report.

Here's A Free Baby Elephant!

Joe Paduda can't blame many of the nation's governors for bowing to the common sense and fiscal reality of expanding Medicaid in their states, even though it can be viewed as distasteful.  The 100% federal financing is free money and their politically connected hospitals prefer Medicaid to uncompensated care.  Many states are likely to cut their Medicaid fee schedules, so providers have one more incentive to go along with testing new reimbursement strategies and delivery models.  All in all, he muses, "this is a very good thing."  Next step, muses the DMCB, is to convince the docs.

The Internet is the most important single development in the history of human communication since the invention of call waiting. - Dave Barry

Time To Take On Medical Tourism By Getting "Lean"

Jonena Relth of Healthcare Talent Transformation points out that the times they are a changin'. The steady increase in medical tourism is challenging the notion that U.S. domiciled health care is the best, especially when international health systems are adopting U.S. methods and employing U.S. trained physicians who are using state-of-the-art electronic health records that are modeled on U.S systems. The salvation, according to Ms. Relth, is the "Lean" approach that, according to a LinkedIn discussion group, helps providers 1) put patients first, 2) cut waste and 3) eliminate tasks that don't add value.  The DMCB's experience leads it to believe that many of its physician colleagues can accomplish much of that third goal by staying away from LinkedIn.  Maybe it's time to change its mind.

"There is science, logic, reason; there is thought verified by experience. And then there is California." - Edward Abbey

California's Health Insurance Exchange Chassis Unveiled. Next Up: The Hard Part

Health reform advocate Anthony Wright of California's Health Access Blog really extols the virtues of Covered California, the Golden State's health insurance exchange web site. Anthony can be forgiven for his use of terms like "conveniently," "breakthrough," "easier" and "bold" because the site's very existence is an important step forward in having a real functioning web presence where consumers can actually buy health insurance. Whether this leads to marketplace transparency, consumer ease-of-use and increased insurance coverage for Californians remains to be seen. The DMCB took the web site's calculator for a test drive and discovered it and the spouse's unsubsidized monthly premium would be $1723 per month, which is about $700 more than it currently pays in Pennsylvania. 'Nuff said.

A Ballooning Benefit Bonanza, Courtesy of Sacramento

Speaking of California, John Goodman of his eponymously named blog examines the state's tax policy, blaming it for a plethora of generous employee benefits. Since higher wages are taxable, loopy loopholes are prompting companies to compensate their employees with home cleaning, personal trainers and the daily delivery of fresh fish. Mr. Goodman faults the unraveling of the 1980's tax reform movement and suggests now is the time for a "progressive flat tax."  Now is also the time for the DMCB Inc. Board of Directors to consider installing a tax deductible gas-powered backyard fire-pit for its two employees. 

Income from Injuries

And Calfornia doesn't stop there. Jon Coopelman of the Workers Comp Insider Blog writes that professional athletes from across the U.S. have discovered that California's generous worker's comp law allows out-of-state players to file claims long after any in-state injury that could have contributed to a disability. Thanks to clever attorneys and vague inclusion criteria, its not hard for any ex-jock who played in the state to convince a California judge that a sports team should cover all future related medical expenses. Jon says its time for the California legislature to stop the abuse and for sports teams to address this in their labor contracts. Until then, the DMCB  invites readers to pay $6 to play to enter an upcoming wiffle ball tourney in Golden Gate Park; participants will receive $1 in California taxable income, $5 worth of beer and a certificate of a compensible injury. Date TBA.

How Much Is That Hospital CEO Worth?

Roy Poses of Health Care Renewal looks at examples of small town hospital CEOs being compensated with lavish pay. Dr. Poses is particularly exasperated because the hospitals are not only public, but they've had to make tough trade-offs between being profitable and having enough nurses and docs to care for their underserved populations. Roy has little difficulty finding numerous news reports - and most are from California -  that amply demonstrate that there is little correlation between hospital administrators' $800K salaries and their institutions' financial performance. Roy blasts the gimmicky talking points that have been used justify these outlandish compensation packages, the cluelessness of hospital boards and the public's need to wake up and smell this coffee. The DMCB looks forward to what Roy discovers in 2015 when he compares ACOs' financial success with their executives' compensation packages.

 "Beware of the young doctor and the old barber." - Benjamin Franklin

Strange Bedfellows

Did you know that 15 new allopathic and 10 osteopathic medical schools have opened since 2002 and that most operate campuses located in Republican Congressional districts?  Wing of Zock's James Lewis reviews the political implications of this, pointing out that these Republicans will gain a new appreciation for the value of our national health care infrastructure. What's more, they'll probably be reluctant to go along with their House colleagues' enthusiasm to reduce the U.S. budget with sacrifices in graduate medical education funding. What delicious irony!

"Bollocks!" An oft-heard exclamation "with a long and distingished history." - Wikipedia

Merry Old En-gland?

Ouch!  The InsureBlog's Mike Feehan looks at a London Daily Mail report on the lowball rate of £20,000 that is used by the Brits' National Health Service when it needs to compensate men for a nutty type of wrong side surgery.  The DMCB points out that one historical explanation for higher U.S. jury awards is the need to compensate for future medical services.  That's less necessary, thanks to the NHS' universal coverage.  The comments that follow testily debate whether the incidence of this complication is higher in the Sceptered Isles compared to the U.S.   The DMCB will never be able to think about NHS "budget cuts" in quite the same way.

That's it for this HWR.  Mark your calendar for the next iteration, due to appear on David Williams' smartly written Health Business Blog on March 13!

Seven Things You Need to Know About 2011 Health Care Spending

If you're interested in learning more about the latest U.S. health care cost trends, everything you need to know is in this article in the January 2015 issue of Health Affairs.

Or you could rely on the Disease Management Care Blog to point out the article's 7 most important points.  Use them to impress your colleagues and stymie your foes:

1) The data only go up to 2011; we'll have to wait another year before we'll know about 2015.

2) 2011 health care spending, as a percent of gross domestic product, remained at 17.9%.  The overall economy was slow and that took its toll on the health care sector.

3) That comes out to $2.7 trillion or $8,680 in health care spending per person.

4) While the percent remained stable, the economy experienced modest growth in 2011. The health care sector, thanks to an overall growth rate of 3.9%, kept pace. Prices for services grew less than the demand for services.  As we grow older, demand is likely to grow.

5) Medicare and private insurance grew faster than the economy, which was offset by Medicaid cost cutting by the states.

6) If the past is any guide, when the U. S. economy rebounds, health care spending is likely to accelerate and resume its march toward becoming 20% of GDP.

7) The relative stabilization of 2011 health care costs is independent of the Affordable Care Act.  Many of its important provisions (such as the mandate) don't kick in until 2015.

Medicaid Disease Management: No Impact on Emergency Room Utilization or Inpatient Costs for Enrollees with Diabetes?

Regular readers of the Disease Management Care Blog know that Medicaid is coming. While many of the nation's Governors have declined President Obama's invitation to run Medicaid the Affordable Care Act way, others have agreed to use the ACA's generous funding to enroll millions of their indigent citizens into this vastly expanded public insurance program.

"No problem!" says the disease management vendors.  For years, they've been offering their services to state Medicaid programs and would be happy to expand their contracts.

Unfortunately, an article by Matthew Conti that was just published in the journal Health Services Research suggests that that may not be a good idea.  The article's title is Effect of Medicaid Disease Management Programs on Emergency Admissions and Inpatient Costs.  The only thing that's missing are the words "The Lack of Any" at the front of that sentence.
   
The article studied the impact of diabetes "opt-out" disease management on diabetic patients' emergency room utilization and admissions in three states' Medicaid programs: Washington (started in 2002), Texas (started in 2004), and Georgia (started in 2005).

These states with were compared to states without diabetes disease management.  These control states were selected on the basis of baseline Medicaid enrollment trends that were similar to the three study states. These control states were Hawaii, Kentucky, Massachusetts, Maryland, Maine, North Carolina, Nebraska, South Carolina and Tennessee.

To perform the comparison, Dr. Conti used the Agency for Health Care Research and Quality's (AHRQ) National InPatient Sample (NIS) from the Health Care Cost and Utilization Project ("HCUP"). These databases contain patient-level and longitudinal hospital information on inpatient stays, including cost, payer, admission type (e.g., emergency, urgent and elective), age, gender, primary payer, and total charges. The span of data that was used went from 2000 through 2008.

A complicated pre-post "difference in differences" model was used to compare baseline vs. follow-up:

1) total inpatient charges/Medicaid enrollment (which averaged $430 per diabetic enrollee, with a 95% confidence interval of $265 to $700) and

2) emergency admissions/inpatient admissions (a ratio of 0.37 per admission with a standard deviation of plus or minus 0.12)  All Medicaid enrollees with diabetes were included in the analysis, whether or not they had been enrolled or opted out.  The author used this approach figuring that if a statewide disease management program enrolled up to a third of eligible persons with diabetes (that was the case in Texas), there should have been an observable impact on the entire population. That's the approach favored by the Disease Management Purchasing Consortium.
 
The results?  No state with disease management had lower emergency room utilization or inpatient costs for their Medicaid enrollees with diabetes. The DMCB couldn't find a table with numbers, but the figures (which can't be reproduced without permission) show little impact over time.

What can readers conclude?  Assuming that, during the period of study, the three states' Medicaid programs suffered from the program's endemic issues of underpayment to providers with a relative lack of access to primary care:

1. "Blanket" call-everyone telephonic disease management cannot make up for fee-for-service Medicaid's shortfalls.  It remains to be seen if the ACA's revitalization of Medicaid will make up for this and increase the parallel impact of disease management. 

2) This also means that Medicaid's experience with disease management can't be generalized to other types of insurance with better provider payment rates and patient access to care.

That being said, the DMCB has two concerns:

1. If the DMCB is reading this right, it appears all persons of any age with diabetes were included in the study, including Type 1 diabetics.  If that's correct, that could have also blunted the impact of any disease management program, since children are over-represented in Medicaid and the impact of remote telephonic coaching in Type 1 is widely viewed (even among the disease management vendors) to be ineffective.  Insulin-requiring kids need lots of face-to-face hands-on care.

2. The DMCB is unfamiliar with the three study states' disease management programs, but if they were set up the "old fashioned way" to contact all persons with diabetes without the modern regard to future risk and "impactibility," then it's little wonder that the programs failed.  State-of-the-art population health management tailors its programs by focusing on subsets of persons with chronic conditions that are most likely to benefit.  Any impact on emergency room use or inpatient charges for these patients would be lost in the data "noise" of everyone else's utilization.

Should Medicaid programs that are facing huge jumps in enrollment abandon Medicaid as a result of this study?  Based on this study, the DMCB doesn't think so.  The findings are interesting, but more research is needed.
Leaderboard